Central Cord Syndrome
Emergency evaluation, diagnosis, and management
- Audience
- Orthopaedic residents, Emergency physicians, PAs / APPs
- Duration
- 45 minutes (paced estimate ~54 min)
- Slides
- 51 across 10 sections
- References
- 95 verified · 9 attributed images
- Presenter
- Aaron Wey, MD, FAAOS, FACS
- Version
- 1.0 · ready
- Created
- 2026-09-26
- Last updated
- 2026-09-26
- Literature reviewed through
- September 2026
Research record: research/central-cord-syndrome/
Learning objectives
- Recognize the clinical pattern of central cord syndrome at the bedside and perform and document an ISNCSCI examination, including sacral sparing and AIS grade.
- Explain the modern understanding of the mechanism: hyperextension pincer compression of a stenotic canal with lateral-column white-matter injury, and why the hands are affected first.
- Select imaging appropriately: CT as the primary study, MRI when a deficit exists, and interpret the MRI findings that drive prognosis and surgical decisions.
- Deliver evidence-based initial management: hemodynamic targets, the current position on steroids, airway and bladder care, VTE prophylaxis, and a structured spine consultation.
- Summarize the evidence on operative versus nonoperative treatment and the timing of decompression, and state what the 2024 guidelines recommend and how strong that evidence is.
- Counsel patients and families on expected recovery, its predictors, age-related mortality and common complications.
Central Cord Syndrome
Emergency evaluation, diagnosis, and management of the most common incomplete spinal cord injury
Outline
- 1.Introductionslide 1
- 2.Why it mattersslide 4
- 3.Anatomy & mechanismslide 7
- 4.Recognitionslide 13
- 5.Imagingslide 21
- 6.Initial managementslide 27
- 7.Surgery & timingslide 33
- 8.Prognosisslide 40
- 9.Casesslide 44
- 10.Summaryslide 48
All slides
Central Cord Syndrome
Emergency evaluation, diagnosis, and management of the most common incomplete spinal cord injury
A 72-year-old man trips on a curb, strikes his forehead, and walks into your department. His legs work. He cannot button his shirt.
His cervical CT is read as “degenerative changes, no acute fracture.”
Learning objectives
- Recognize the pattern at the bedside and perform a proper ISNCSCI examination
- Explain the mechanism and why the hands suffer first
- Choose imaging correctly: CT first, MRI when there is a deficit
- Deliver evidence-based initial management and a structured consult
- State what the 2024 guidelines say about surgery and timing, and how strong that evidence is
- Counsel patients on recovery, predictors, and complications
Why it matters
The most common incomplete cord injury, in the fastest-growing trauma population
Common, and getting more common
How the concept evolved
- 1954Schneider describes the syndrome and links it to hyperextension Schneider 1954
- 1971Bosch: favourable natural history in incomplete tetraplegia Bosch 1971
- 1992Quencer: MRI–pathology shows white-matter axonal injury, not central hemorrhage Quencer 1992
- 2010Lenehan: early surgery for stenotic CCS without instability gains 6 motor points Lenehan 2010
- 2013–17AANS/CNS and AOSpine guidelines: MAP targets, no steroids, early surgery as an option Fehlings 2017
- 2022Badhiwala: propensity-matched CCS cohort favours surgery within 24 h Badhiwala 2022
- 2024AO Spine/Praxis: early surgery preferred; MAP range widened Fehlings 2024
Anatomy and mechanism
Why the hands, and why no fracture
An incomplete cervical cord injury with disproportionately greater weakness in the upper than the lower extremities, variable sensory loss, and variable bladder dysfunction.
Classically after hyperextension of a stenotic cervical spine, often without fracture or dislocation. Schneider 1954 Anderson 2015
The lateral corticospinal tract is the target
Axial cervical cord, schematic. Original diagram.
- Gray matter butterfly; white matter columns carry the long tracts
- Lateral corticospinal tract in the lateral column: the main descending motor pathway
- Textbooks drew cervical fibres medial and sacral fibres lateral, so a central lesion should spare the legs. Primate studies do not support this lamination. Levi 1996
- Autopsy and MRI show axonal disruption in the lateral columns with the central gray intact. Quencer 1992 Jimenez 2000
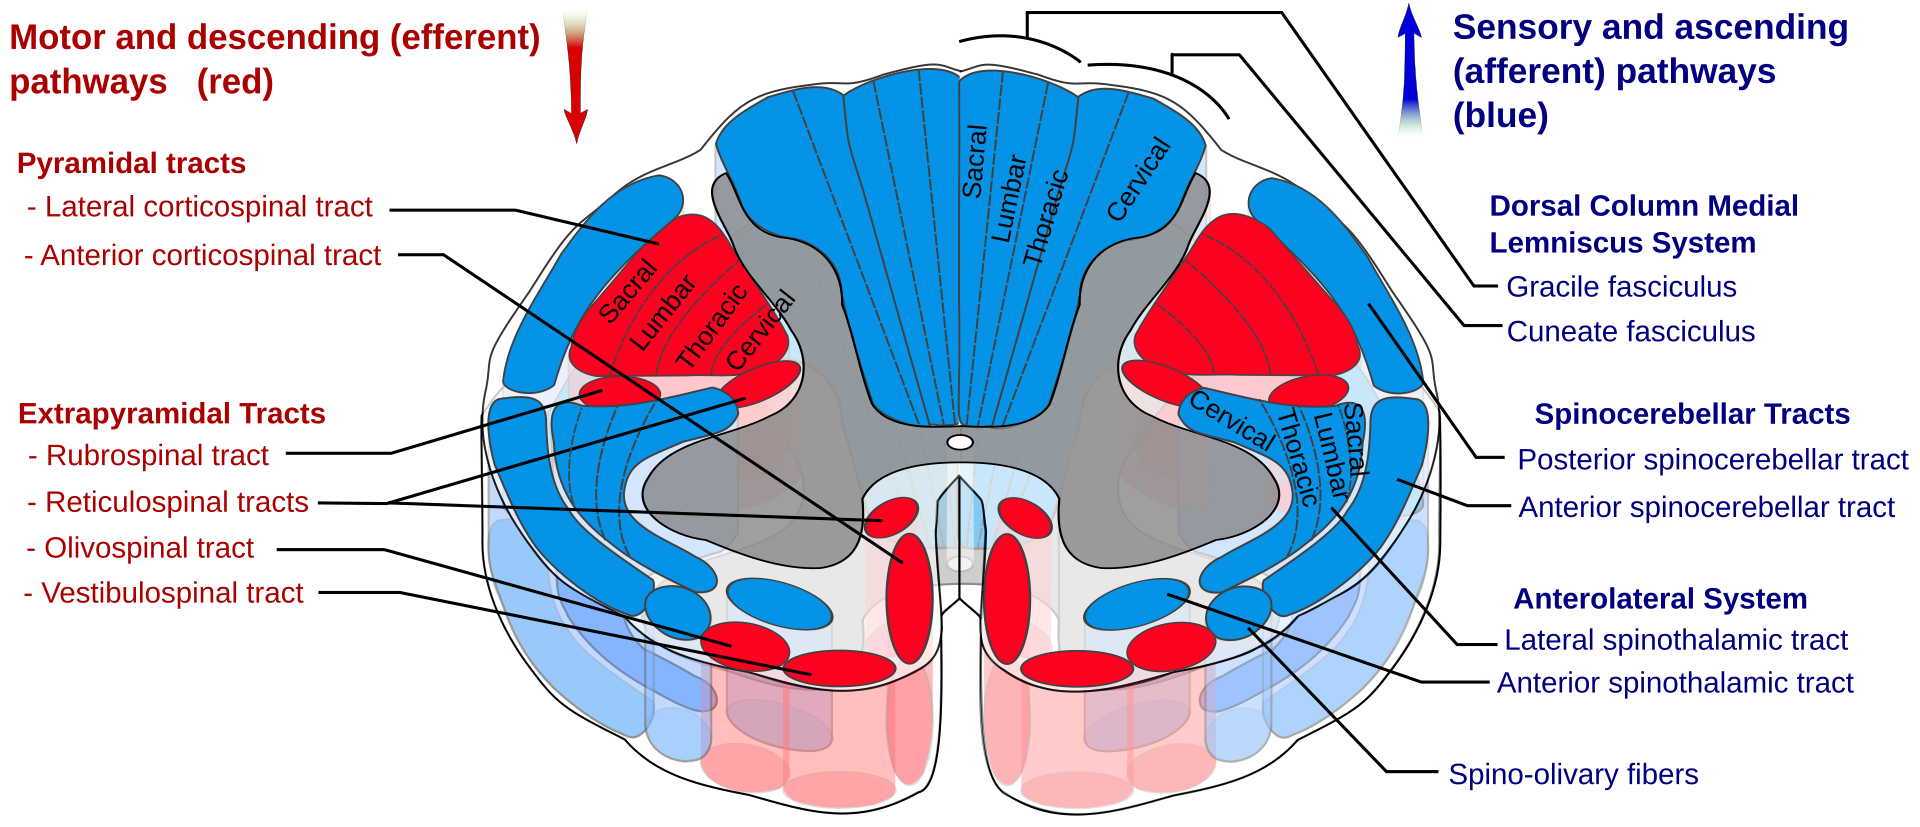
The picture in every textbook
What is wrong with this picture?
Hyperextension in a narrow canal
Sagittal schematic of a spondylotic cervical canal in neutral and extension. Original diagram.
- Spondylosis narrows the canal from the front: disc–osteophyte complexes, sometimes OPLL
- Extension shortens the canal and buckles the thickened ligamentum flavum inward from behind
- The cord is pinched transiently between the two; the spine returns to neutral and the CT looks degenerative, not traumatic
Older versus younger patient
Older adult with spondylosis
- Low-energy fall, forehead or chin impact
- Pre-existing canal stenosis, sometimes OPLL
- Usually no fracture or dislocation on CT
- Comorbidities, anticoagulation, frailty
- Surgical decision is about persistent compression, not instability
Younger patient with high-energy trauma
- Motor vehicle crash, diving, sport, fall from height
- Fracture, facet dislocation or traumatic disc herniation
- Structural instability drives the operative decision
- Polytrauma and head injury may obscure the examination
- Surgery ≤ 24 h benefits this group most consistently Guest 2002
Guest 2002: surgery within 24 h improved motor recovery in disc-herniation and fracture cases but not in stenosis/spondylosis. Guest 2002
Recognition in the emergency department
History, examination, and the definitions nobody agrees on
What the patient tells you
- Hands first: weak grip, clumsy fingers, cannot button, cannot hold a cup
- Burning or “gloved” dysesthesia of the hands and forearms is common and distressing
- Legs relatively spared: many patients are ambulatory, sometimes unsteady
- Urinary retention in a proportion; ask, and check a bladder scan
- Sacral sparing: perianal sensation and voluntary anal contraction preserved
- Neck pain may be mild or absent; facial or forehead injury points to extension
Upper versus lower extremity motor scores
Admission means from Aarabi 2011 (n = 42); threshold from Pouw 2010. Original diagram.
- Each side scores five key muscles per limb, 0–5 each: UEMS and LEMS each run 0–50 Rupp 2021
- The gap is the syndrome. In stenotic CCS the admission means were UE 25.8 and LE 39.8 Aarabi 2011
- A systematic review of 312 patients found a mean 10.5-point gap; ≥ 10 points is the most-used criterion, endorsed by 61% of surveyed surgeons Pouw 2010 van 2010
What counts as central cord syndrome?
| Definition | Source | Strength | Weakness |
|---|---|---|---|
| Descriptive: arms weaker than legs, sacral sparing, variable bladder | Schneider 1954 Schneider 1954 | Clinically intuitive | Not quantified; observer-dependent |
| LEMS − UEMS ≥ 10 motor points | Pouw 2010 Pouw 2010 | Reproducible, most used in research | Excludes milder or atypical cases |
| LEMS − UEMS ≥ 5 motor points | Badhiwala 2022 Badhiwala 2022 | Captures more patients | Different cohorts from the ≥ 10 studies |
| Any adult cervical SCI without fracture or dislocation | Avila & Hurlbert 2021 Avila 2021 | Separates stable from unstable spines | Ignores the neurological pattern |
| Central Cord Injury Scale / Central Cord Score | Hohl 2010; Ramey 2021 Hohl 2010 Ramey 2021 | Adds MRI and function for prognosis | Small derivation cohorts |
There is no consensus definition. Prognostic studies show that AIS grade predicts outcome better than the CCS label itself. Pouw 2011 Engel-Haber 2023
The ISNCSCI examination in the trauma bay
What to do
- Ten key muscles each side, graded 0–5: C5 elbow flexion to T1 finger abduction, L2 hip flexion to S1 plantar flexion
- Light touch and pinprick in 28 dermatomes each side, including S4–5
- Sacral examination: S4–5 sensation, deep anal pressure, voluntary anal contraction
- Determine the neurological level and the AIS grade; record the time
Why it matters
- The admission motor score is the strongest predictor of recovery in every series Aarabi 2011 Dvorak 2005 Aarabi 2021
- AIS C versus D changes the surgical conversation Lenehan 2010 Badhiwala 2022
- A documented baseline is the only way to detect deterioration
- Repeat at 24–72 h: the early examination can be confounded by pain, sedation and spinal shock Ditunno 2004
ASIA Impairment Scale
Most central cord patients are AIS C or D. Definitions per ISNCSCI 2019. Rupp 2021
Spinal shock versus neurogenic shock
Spinal shock
- Transient loss of reflexes and tone below the injury
- Evolves in phases over hours to weeks; bulbocavernosus reflex returns first Ditunno 2004
- Can make an incomplete injury look complete on the first examination
- Does not cause hypotension
Neurogenic shock
- Hypotension with inappropriate bradycardia from loss of sympathetic outflow
- Reported incidence varies widely with definition; about 29% in cervical SCI by combined criteria Ruiz 2018
- Hypovolemia from other injuries is the great confounder: look for bleeding first
- Treat with volume, then vasopressors with chronotropic activity; atropine or pacing for bradycardia
A 68-year-old woman falls down three steps and has a laceration on her forehead. She walks into the department. Both hands are weak (grip 3/5) with burning paresthesia; legs are 5/5; perianal sensation is intact. Her cervical CT is reported as spondylosis without fracture. What is the next step?
- AClear the cervical collar using NEXUS criteria and discharge with hand therapy follow-up
- BFlexion–extension radiographs to exclude instability
- CMRI of the cervical spine and a spine surgery consultation now
- DNerve conduction studies to evaluate for bilateral carpal tunnel syndrome
Imaging
CT finds the fracture. MRI finds the injury.
Who gets what
Flexion–extension radiographs have no role in the acute setting with a deficit.
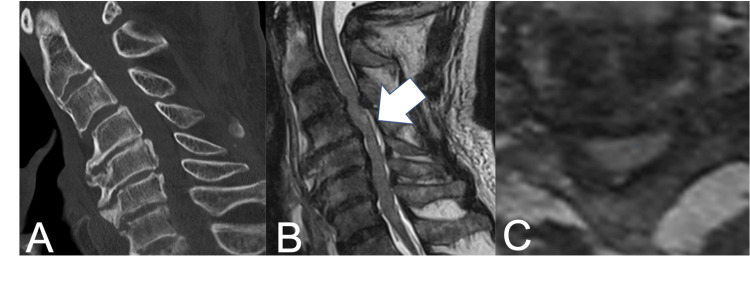
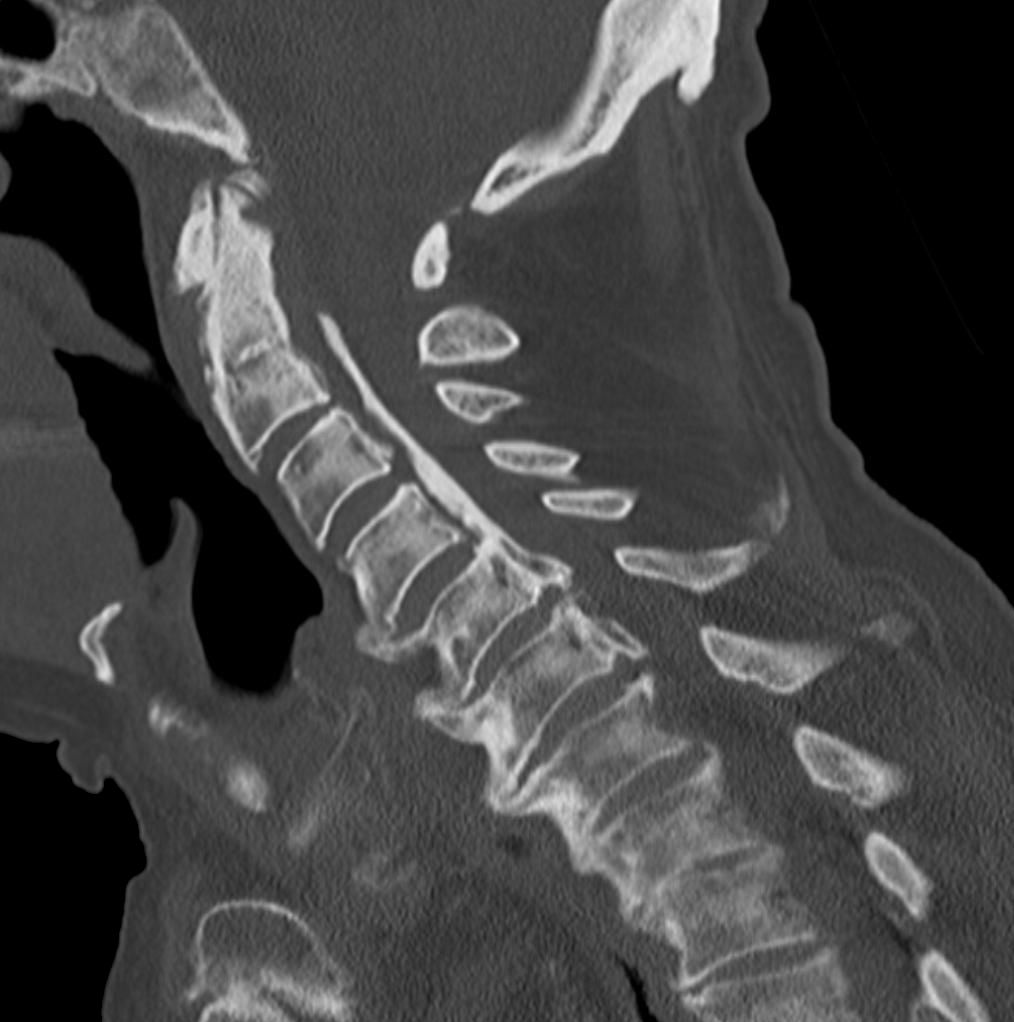
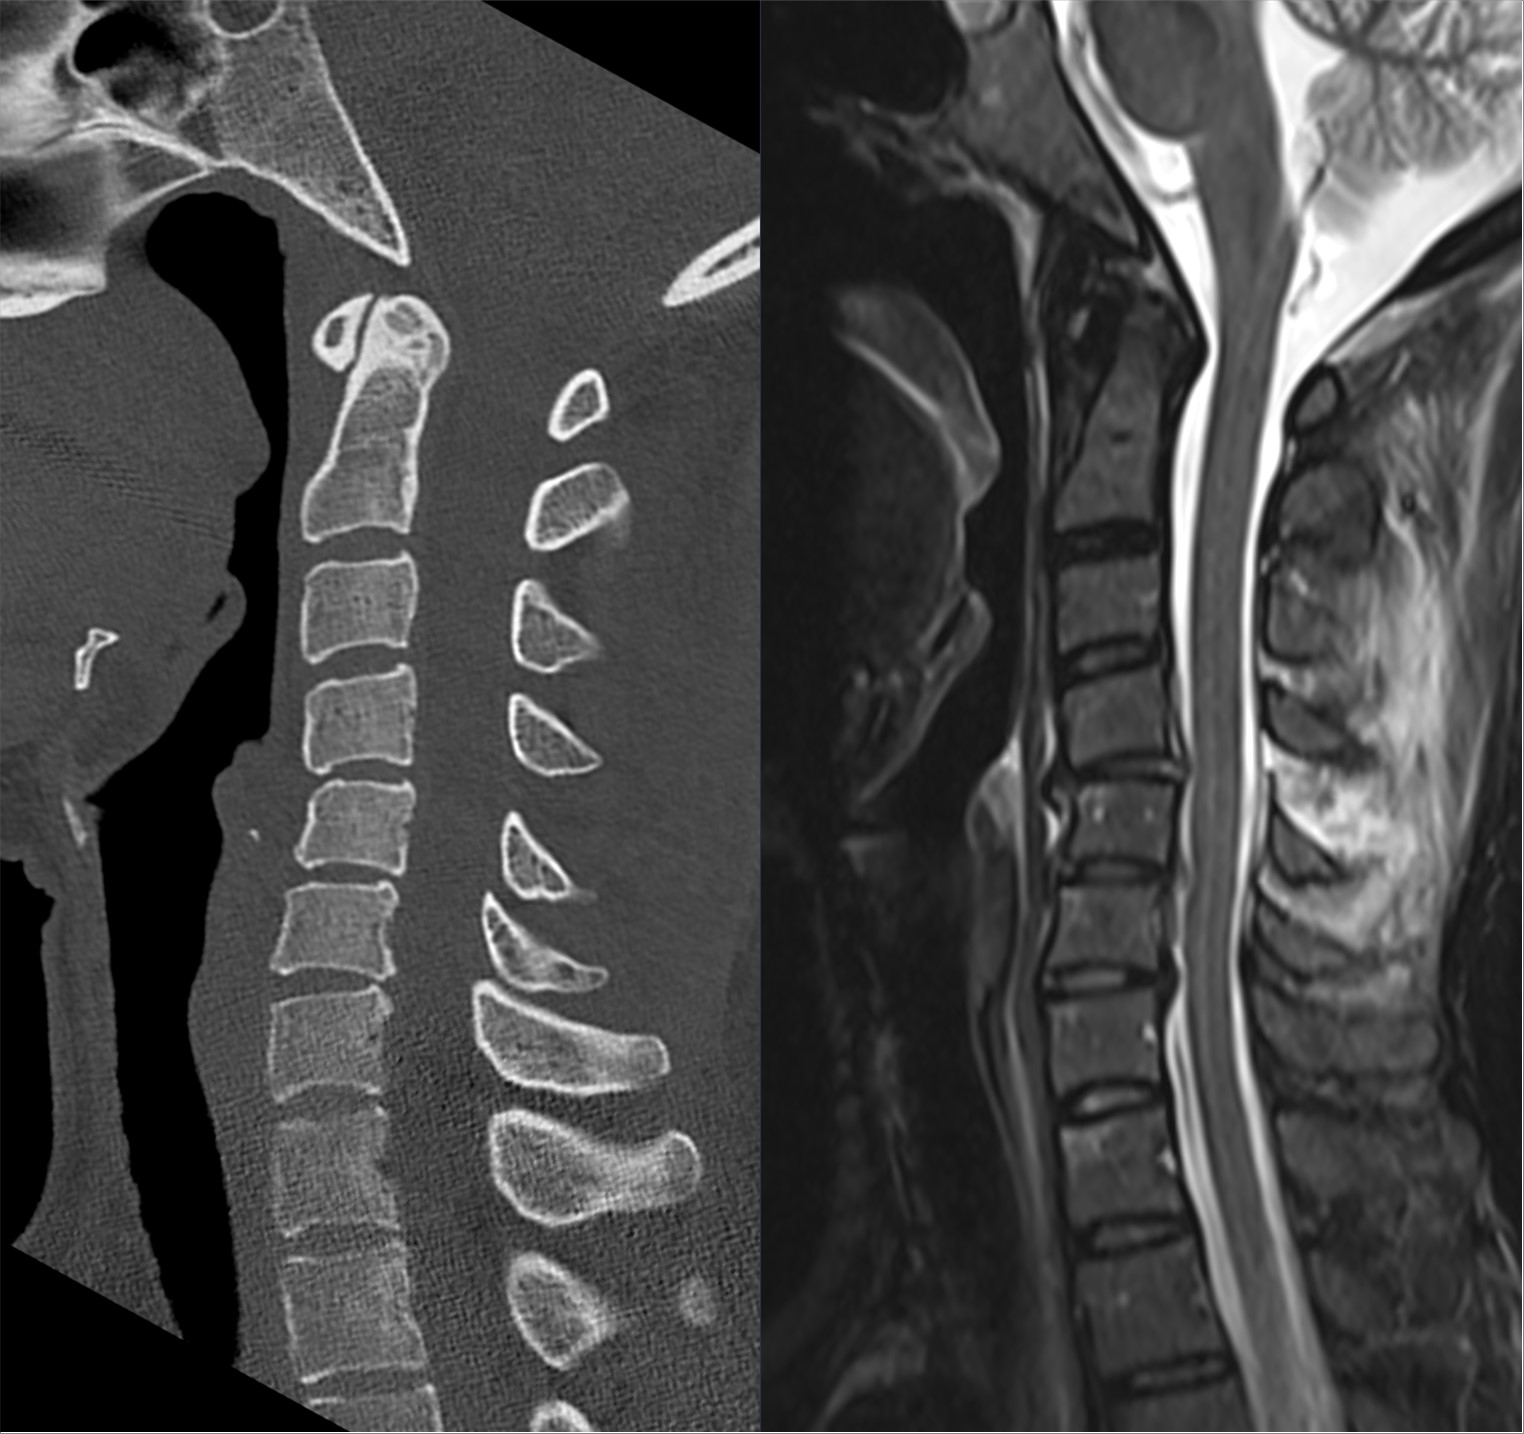
Normal CT. Abnormal cord.
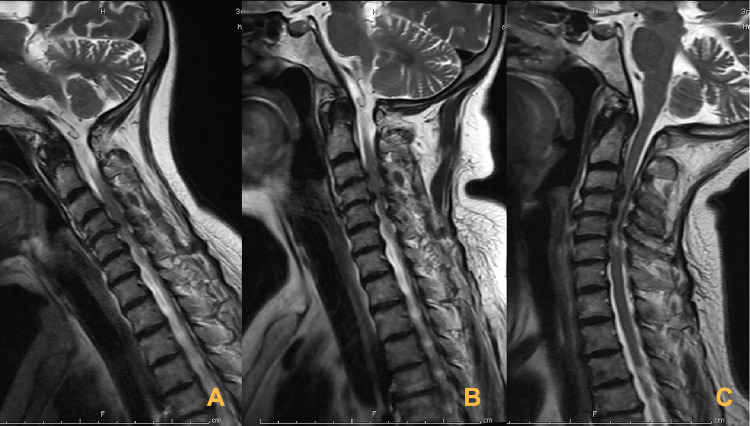
The mechanism, caught on MRI
What matters on the MRI
- T2 cord signal: edema is expected; hemorrhage on T2* or T1 predicts worse recovery Bozzo 2011 Wilson 2012
- Length of intramedullary hyperintensity: longer lesions predict worse motor outcome and pain Aarabi 2011 Aarabi 2021
- Degree of compression: midsagittal diameter and maximum canal compromise predict outcome Aarabi 2011
- Persistent compression after injury is the surgical target; document its level and cause
- STIR/fat-saturated sequences: ligamentous injury, interspinous edema, disc disruption
- The BASIC score grades axial T2 involvement 0–4 and tracks with AIS grade Talbott 2015
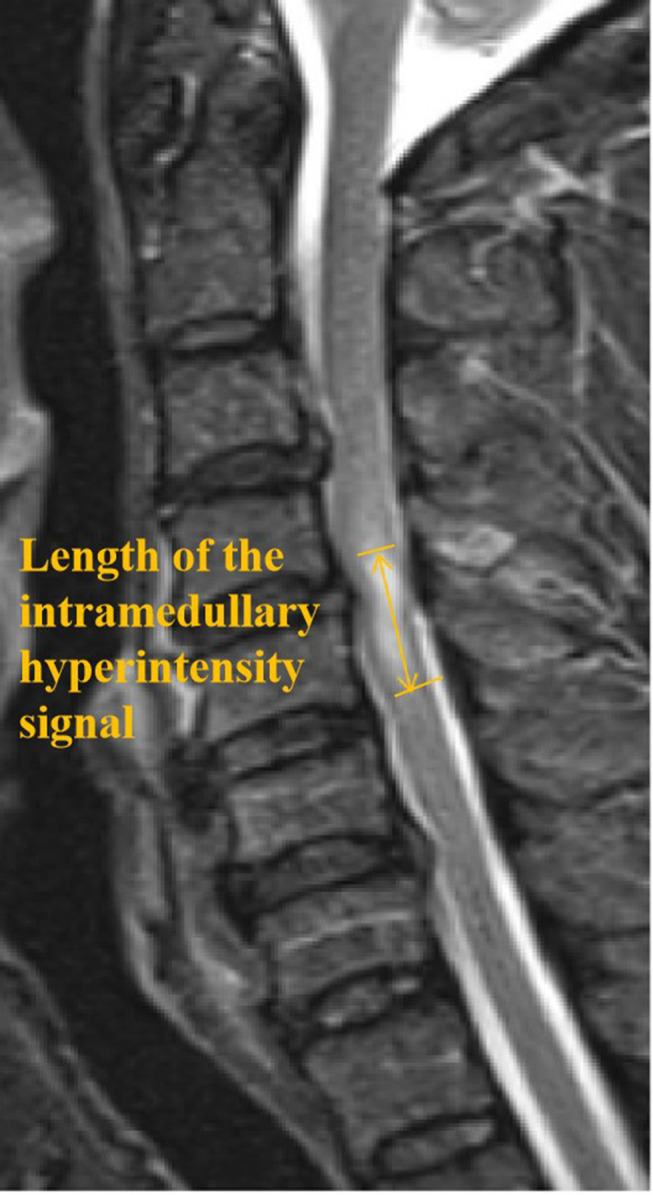
What the CT can add
- Spondylotic stenosis without fracture: the majority in older adults
- OPLL: ossified posterior longitudinal ligament, common in East Asian populations, may fracture through the ossified mass
- Traumatic disc herniation: young patient, normal bone, acute cord compression
- Fracture or facet dislocation: unstable; reduce and stabilise
- Ankylosed spine (DISH, ankylosing spondylitis): extension fractures through a fused column are unstable and easily missed
- Classify structural injuries with SLIC or the AOSpine subaxial system to frame the operative decision Vaccaro 2007 Vaccaro 2016
Initial management
Protect the cord, perfuse the cord, and call early
Emergency department pathway
Mean arterial pressure targets
Guideline MAP ranges after acute SCI. Ryken 2013 Kwon 2024 Hawryluk 2015 Readdy 2015
Methylprednisolone
Should this patient receive high-dose steroids?
| Study | Design | N | Comparison | Key finding | Limitation |
|---|---|---|---|---|---|
NASCIS II 1990 Bracken 1990 | RCT, 3 arms | 487 | MPSS 30 mg/kg + 5.4 mg/kg/h × 23 h vs naloxone vs placebo | No overall benefit; post-hoc: modest motor gain if given < 8 h | Subgroup analysis; small absolute effect |
NASCIS III 1997 Bracken 1997 | RCT | 499 | MPSS 24 h vs 48 h vs tirilazad | 48 h regimen: motor gain if started 3–8 h | No placebo; more sepsis and pneumonia with 48 h |
Cochrane (Bracken) 2012 Bracken 2012 | Systematic review | — | MPSS vs control | Modest motor benefit within 8 h | Authored by the NASCIS lead investigator |
Evaniew 2016 Evaniew 2016 | Meta-analysis, GRADE | 4 RCTs, 17 obs. | MPSS vs no steroid | No long-term motor benefit; ↑ GI bleeding in observational data | Low to very low confidence |
AANS/CNS 2013 Hurlbert 2013 | Guideline | — | — | Level I recommendation against MPSS | Criticised for over-reading harm data |
AOSpine 2017 Fehlings 2017 | Guideline | — | — | Suggest 24 h MPSS may be offered as an option if < 8 h; not after 8 h; never 48 h | Weak recommendation |
Any benefit is small, confined to the first 8 hours and rests on post-hoc analyses; harm signals include infection, hyperglycemia and GI bleeding, which weigh heavily in older patients.
Not a standard of care. Do not give steroids to a central cord patient presenting after 8 hours. Within 8 hours, follow your institutional protocol and the consulting surgeon; if used, it is the 24-hour regimen, never 48 hours.
The rest of the first 24 hours
- Bladder: catheter early; retention and distension are common and can drive autonomic instability
- Respiratory: serial vital capacity, incentive spirometry, aspiration precautions; edema can ascend over 48–72 h
- VTE prophylaxis: mechanical now, pharmacological within 72 h once bleeding risk is settled Dhall 2013
- Skin: turn schedule and pressure relief from the first hour; older skin breaks down fast
- Temperature and glucose: avoid hyperthermia and hyperglycemia
- Neurological checks every 1–2 h initially; any decline is a call to the surgeon
- Pain and dysesthesia: multimodal analgesia; avoid over-sedation that hides deterioration
What the spine surgeon needs to hear
- Mechanism and time of injury: the clock for the 24-hour window starts at injury, not at arrival
- Examination: AIS grade, UEMS and LEMS, sacral sparing, bladder, and whether it is stable, improving or worsening
- CT: fracture, dislocation, OPLL, ankylosis, canal size
- MRI: level and cause of compression, cord signal, ligamentous injury
- Physiology: blood pressure, pressor requirement, airway status
- The patient: age, comorbidities, anticoagulants, baseline function, goals of care
Operative versus nonoperative treatment, and when
Seventy years of controversy, and where the evidence stands in 2026
Who is treated nonoperatively, and who is not
Nonoperative management is reasonable
- Stable spine: no fracture, dislocation or ligamentous disruption
- AIS D with an improving examination in the first days Lenehan 2010
- Little or no persistent cord compression on MRI
- Prohibitive medical risk or goals of care that exclude surgery
- Requires serial examinations and a low threshold to reconsider
Surgery is indicated or favoured
- Unstable injury: fracture, dislocation, disrupted posterior ligaments, ankylosed spine
- Persistent compression with a significant deficit, particularly AIS C Lenehan 2010 Badhiwala 2022
- Neurological deterioration or a plateau without recovery
- Traumatic disc herniation compressing the cord Guest 2002
- Persistent compression from stenosis or OPLL after initial recovery: elective decompression to prevent recurrence and myelopathy
No randomized trial compares surgery with nonoperative care for central cord syndrome. These are consensus positions drawn from observational data and guidelines. Aarabi 2013 Yelamarthy 2019
When should the cord be decompressed?
Early (< 24 h) versus late surgery
| Study | Design | N | Comparison | Key finding | Limitation |
|---|---|---|---|---|---|
STASCIS 2012 Fehlings 2012 | Prospective cohort, all cervical SCI | 313 | < 24 h vs ≥ 24 h | ≥ 2-grade AIS gain 19.8% vs 8.8% (adj. OR 2.8) | Not randomised; 71% follow-up |
Lenehan 2010 Lenehan 2010 | Ambispective, stenotic CCS without instability | STSG database | < 24 h vs later | +6.3 motor points at 12 months | Observational; small effect |
Badhiwala 2021 Badhiwala 2021 | Pooled IPD, 4 prospective datasets | 1,548 | < 24 h vs ≥ 24 h | +4.0 motor points at 1 year; plateau after 24–36 h | All SCI, not CCS-specific |
Badhiwala 2022 Badhiwala 2022 | Propensity-matched CCS cohort | 186 | < 24 h vs ≥ 24 h | +2.3 UE motor points; AIS C +9.5 total; AIS D no difference | Younger cohort (mean 48); CCS defined as ≥ 5-point gap |
Aarabi 2021 Aarabi 2021 | Retrospective, stenotic CCS, MRI-confirmed decompression | 101 | ≤ 24 h vs 25–72 h vs > 72 h | No effect of timing; admission motor score predicted outcome | Single centre; AIS C/D only |
Sattari 2024 Sattari 2024 | Meta-analysis, CCS | 5,619 (9 studies) | < 24 h vs ≥ 24 h | +4.9 motor points at 1 year; fewer VTE and complications; shorter stay; no mortality difference | Observational inputs; moderate certainty |
Moderate-quality observational evidence that decompression within 24 hours improves motor recovery across SCI, with a smaller but consistent signal in central cord syndrome, concentrated in AIS C patients and those with structural compression. Some stenotic cohorts show no timing effect.
Treat a central cord patient with persistent compression and a meaningful deficit as time-sensitive: consult at diagnosis, resuscitate quickly, and aim for surgery within 24 hours when the patient is fit. AIS D patients with an improving examination can be observed.
The window closes over the first 24–36 hours
Illustrative curve shaped after the pooled analysis of 1,548 patients; not plotted from raw data. Badhiwala 2021 Badhiwala 2019
What the guidelines actually say
| Guideline | Recommendation on timing | Evidence |
|---|---|---|
| AANS/CNS 2013 Aarabi 2013 | Early reduction of fracture-dislocation; early surgical decompression of the compressed cord | Level III |
| AOSpine 2017 Fehlings 2017 | “We suggest that early surgery be considered as a treatment option in adult patients with traumatic central cord syndrome” | Low |
| Spinal Cord Society / STSG 2019 Yelamarthy 2019 | Position statement favouring early surgery in selected patients with persistent compression | Systematic review |
| AO Spine / Praxis 2024 Fehlings 2024 | Early surgery (≤ 24 h) offered as the preferred option for adult acute SCI regardless of level; no recommendation on ultra-early surgery | Moderate (RR 2.76 for ≥ 2-grade AIS gain at 6 months; +4.5 motor points) |
The 2024 recommendation applies to acute SCI as a whole; the guideline does not carve out a separate rule for central cord syndrome.
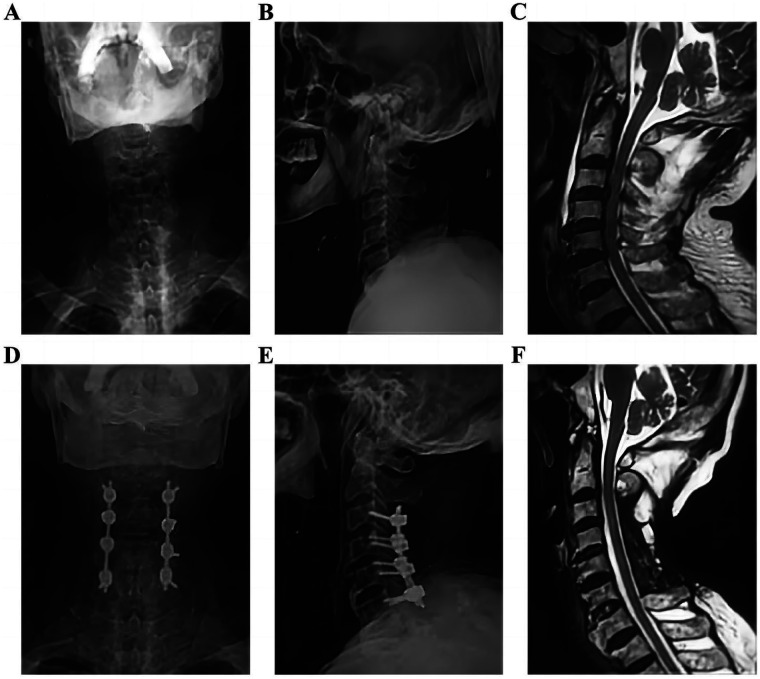
Choosing the operation
- Match the approach to the compression: anterior for one- or two-level disc-osteophyte disease, posterior for multilevel stenosis or OPLL with preserved lordosis
- ACDF is the most common procedure in national data Brodell 2015; laminoplasty or laminectomy with fusion for multilevel disease
- Instability dictates fusion; reduce dislocations promptly
- Kyphosis limits the value of posterior decompression alone; consider combined approaches
- Confirm decompression postoperatively; residual compression is associated with poorer recovery Aarabi 2021
- Approach selection is surgeon judgment; comparative evidence is retrospective Divi 2019
A 61-year-old man falls from a ladder. Examination at 4 hours: UEMS 18, LEMS 38, sacral sparing present, most key muscles below the level are grade 2 (AIS C). CT: multilevel spondylosis, no fracture. MRI: C4–5 and C5–6 compression with T2 signal at C4–5, no ligamentous injury. He is hemodynamically stable. Which statement best reflects current evidence?
- ASurgery is not indicated because the spine is stable
- BObservation for 2 weeks is preferred because central cord patients recover spontaneously
- CDecompression within 24 hours is reasonable and, on moderate-quality evidence, is the preferred option
- DSurgery should be delayed until MAP augmentation has been completed for 7 days
Prognosis and complications
What to tell the patient and the family
Most patients improve substantially. Many are left disabled.
What predicts recovery
Favourable
- Higher admission motor score and AIS D Aarabi 2011 Pouw 2011 Dvorak 2005
- Younger age Penrod 1990 Ronzi 2018
- No or short T2 signal change; no hemorrhage Ishida 2002 Wilson 2012
- Preserved hand function, hyperpathia, normal perianal sensation Merriam 1986
- Fewer comorbidities, no spasticity Dvorak 2005
Recovery pattern
- Legs recover first, then bladder, then proximal arms; hands last and least Schneider 1958
- Most gain occurs in the first weeks to months; upper-limb-only injuries without cord signal may recover by 6 weeks Ishida 2002
- Persistent hand dysesthesia and spasticity are the common long-term problems
- AIS grade beats the CCS label as a prognostic tool Pouw 2011
What goes wrong
- 58% of acute SCI patients had a complication in a prospective cohort, most within 14 days; respiratory failure and pneumonia led Grossman 2012
- Respiratory: aspiration, atelectasis, pneumonia; the leading cause of death after CCS Stanley 2023
- Venous thromboembolism: prophylaxis within 72 h; early surgery associated with fewer events Dhall 2013 Sattari 2024
- Urinary retention and infection; bowel dysfunction
- Pressure injury; delirium in older patients; deconditioning
- Neuropathic pain and dysesthesia, spasticity, and the psychological burden of useless hands
- Vasopressor-related cardiac events in older patients Readdy 2015
Two cases
Apply it
The 72-year-old from the first slide
- Decision and course
- AIS D with persistent compression: observation is defensible, early surgery is reasonable; the examination trajectory decides
- By 12 h: grip 3/5, walking with a frame. Anticoagulation reversed; surgery within 24 h offered given persistent severe compression and a diabetic older patient at risk of repeat injury
- C4–5 ACDF at 19 h. Discharged to rehabilitation day 9. At 6 months: walking unaided, grip 4/5, persistent hand dysesthesia, independent with adapted utensils
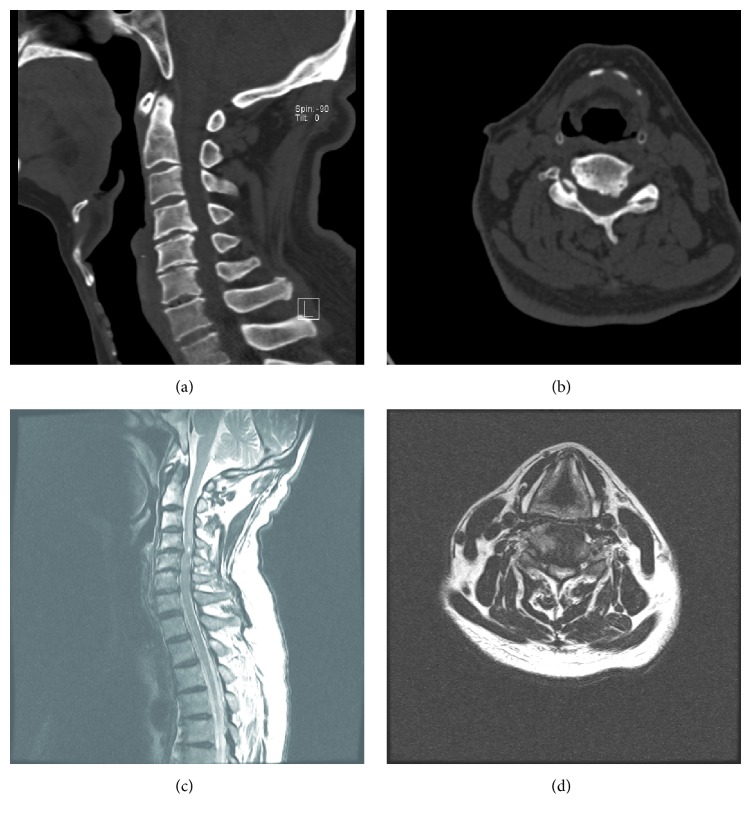
A 24-year-old after a dive
- Course
- Surgery at 7 h from injury after resuscitation; MAP maintained 80–90 for 5 days on norepinephrine; no steroids
- Complications: pneumonia day 4, treated. VTE prophylaxis from day 2
- At 12 months: AIS D, walking unaided, grip 3/5 right and 4/5 left, returned to modified work
An 80-year-old woman with central cord syndrome after a fall (AIS D, stable spine, CT without fracture) arrives 11 hours after injury. Her family asks whether she should receive high-dose methylprednisolone. What do you tell them?
- AYes: NASCIS II showed a clear benefit for all patients treated within 24 hours
- BYes, but only the 48-hour regimen, because she presented late
- CNo: she is outside the 8-hour window, the benefit is uncertain even within it, and the risks are higher at her age
- DOnly if the MRI shows hemorrhage within the cord
Six things to take back to the department
- Older adult, forehead injury, weak hands, walking: that is central cord syndrome until proven otherwise
- It is a lateral-column corticospinal injury from a pincer in a narrow canal; the CT is usually normal
- A deficit means MRI, whatever the CT says; document UEMS, LEMS, sacral sparing and AIS grade with the time
- Perfuse the cord (MAP floor 75–80, avoid dopamine in older patients), protect the airway, catheter, VTE prophylaxis; steroids are not standard
- Call the surgeon at diagnosis: early decompression within 24 h is the preferred option on moderate evidence, strongest for AIS C and structural compression
- Counsel from the AIS grade and the age: most improve, hands recover last, and mortality in the very old is high
Time is spine, but the patient is more than the cord.
Recognise early, image the cord, perfuse it, call early, and treat the older adult as the whole and fragile person they are.
Selected references
1.Schneider RC, Cherry G, Pantek H. The syndrome of acute central cervical spinal cord injury; with special reference to the mechanisms involved in hyperextension injuries of cervical spine. J Neurosurg. 1954;11(6):546-77.
2.Penrod LE, Hegde SK, Ditunno JF Jr. Age effect on prognosis for functional recovery in acute, traumatic central cord syndrome. Arch Phys Med Rehabil. 1990;71(12):963-8.
3.Quencer RM, Bunge RP, Egnor M, Green BA, Puckett W, Naidich TP. Acute traumatic central cord syndrome: MRI-pathological correlations. Neuroradiology. 1992;34(2):85-94.
4.Levi AD, Tator CH, Bunge RP. Clinical syndromes associated with disproportionate weakness of the upper versus the lower extremities after cervical spinal cord injury. Neurosurgery. 1996;38(1):179-83; discussion 183-5.
5.Pouw MH, van Middendorp JJ, van Kampen A, Hirschfeld S, Veth RP, Em-sci study group. Diagnostic criteria of traumatic central cord syndrome. Part 1: a systematic review of clinical descriptors and scores. Spinal Cord. 2010;48(9):652-6.
6.Rupp R, Biering-Sørensen F, Burns SP, Graves DE, Guest J, Jones L. International Standards for Neurological Classification of Spinal Cord Injury: Revised 2019. Top Spinal Cord Inj Rehabil. 2021;27(2):1-22.
7.Hoffman JR, Mower WR, Wolfson AB, Todd KH, Zucker MI. Validity of a set of clinical criteria to rule out injury to the cervical spine in patients with blunt trauma. National Emergency X-Radiography Utilization Study Group. N Engl J Med. 2000;343(2):94-9.
8.Como JJ, Diaz JJ, Dunham CM, Chiu WC, Duane TM, Capella JM. Practice management guidelines for identification of cervical spine injuries following trauma: update from the eastern association for the surgery of trauma practice management guidelines committee. J Trauma. 2009;67(3):651-9.
9.Bozzo A, Marcoux J, Radhakrishna M, Pelletier J, Goulet B. The role of magnetic resonance imaging in the management of acute spinal cord injury. J Neurotrauma. 2011;28(8):1401-11.
10.Aarabi B, Hadley MN, Dhall SS, Gelb DE, Hurlbert RJ, Rozzelle CJ. Management of acute traumatic central cord syndrome (ATCCS). Neurosurgery. 2013;72 Suppl 2:195-204.
11.Ryken TC, Hurlbert RJ, Hadley MN, Aarabi B, Dhall SS, Gelb DE. The acute cardiopulmonary management of patients with cervical spinal cord injuries. Neurosurgery. 2013;72 Suppl 2:84-92.
12.Hurlbert RJ, Hadley MN, Walters BC, Aarabi B, Dhall SS, Gelb DE. Pharmacological therapy for acute spinal cord injury. Neurosurgery. 2013;72 Suppl 2:93-105.
13.Fehlings MG, Wilson JR, Tetreault LA, Aarabi B, Anderson P, Arnold PM. A Clinical Practice Guideline for the Management of Patients With Acute Spinal Cord Injury: Recommendations on the Use of Methylprednisolone Sodium Succinate. Global Spine J. 2017;7(3 Suppl):203S-211S.
14.Fehlings MG, Tetreault LA, Hachem L, Evaniew N, Ganau M, McKenna SL. An Update of a Clinical Practice Guideline for the Management of Patients With Acute Spinal Cord Injury: Recommendations on the Role and Timing of Decompressive Surgery. Global Spine J. 2024;14(3_suppl):174S-186S.
15.Kwon BK, Tetreault LA, Martin AR, Arnold PM, Marco RAW, Newcombe VFJ. A Clinical Practice Guideline for the Management of Patients With Acute Spinal Cord Injury: Recommendations on Hemodynamic Management. Global Spine J. 2024;14(3_suppl):187S-211S.
16.Bracken MB, Shepard MJ, Collins WF, Holford TR, Young W, Baskin DS. A randomized, controlled trial of methylprednisolone or naloxone in the treatment of acute spinal-cord injury. Results of the Second National Acute Spinal Cord Injury Study. N Engl J Med. 1990;322(20):1405-11.
17.Evaniew N, Belley-Côté EP, Fallah N, Noonan VK, Rivers CS, Dvorak MF. Methylprednisolone for the Treatment of Patients with Acute Spinal Cord Injuries: A Systematic Review and Meta-Analysis. J Neurotrauma. 2016;33(5):468-81.
18.Hawryluk G, Whetstone W, Saigal R, Ferguson A, Talbott J, Bresnahan J. Mean Arterial Blood Pressure Correlates with Neurological Recovery after Human Spinal Cord Injury: Analysis of High Frequency Physiologic Data. J Neurotrauma. 2015;32(24):1958-67.
19.Readdy WJ, Whetstone WD, Ferguson AR, Talbott JF, Inoue T, Saigal R. Complications and outcomes of vasopressor usage in acute traumatic central cord syndrome. J Neurosurg Spine. 2015;23(5):574-580.
20.Fehlings MG, Vaccaro A, Wilson JR, Singh A, W Cadotte D, Harrop JS. Early versus delayed decompression for traumatic cervical spinal cord injury: results of the Surgical Timing in Acute Spinal Cord Injury Study (STASCIS). PLoS One. 2012;7(2):e32037.
21.Badhiwala JH, Wilson JR, Witiw CD, Harrop JS, Vaccaro AR, Aarabi B. The influence of timing of surgical decompression for acute spinal cord injury: a pooled analysis of individual patient data. Lancet Neurol. 2021;20(2):117-126.
22.Lenehan B, Fisher CG, Vaccaro A, Fehlings M, Aarabi B, Dvorak MF. The urgency of surgical decompression in acute central cord injuries with spondylosis and without instability. Spine (Phila Pa 1976). 2010;35(21 Suppl):S180-6.
23.Samuel AM, Grant RA, Bohl DD, Basques BA, Webb ML, Lukasiewicz AM. Delayed surgery after acute traumatic central cord syndrome is associated with reduced mortality. Spine (Phila Pa 1976). 2015;40(5):349-56.
24.Aarabi B, Alexander M, Mirvis SE, Shanmuganathan K, Chesler D, Maulucci C. Predictors of outcome in acute traumatic central cord syndrome due to spinal stenosis. J Neurosurg Spine. 2011;14(1):122-30.
25.Dvorak MF, Fisher CG, Hoekema J, Boyd M, Noonan V, Wing PC. Factors predicting motor recovery and functional outcome after traumatic central cord syndrome: a long-term follow-up. Spine (Phila Pa 1976). 2005;30(20):2303-11.
26.Badhiwala JH, Wilson JR, Harrop JS, Vaccaro AR, Aarabi B, Geisler FH. Early vs Late Surgical Decompression for Central Cord Syndrome. JAMA Surg. 2022;157(11):1024-1032.
27.Badhiwala JH, Witiw CD, Wilson JR, da Costa LB, Nathens AB, Fehlings MG. Treatment of Acute Traumatic Central Cord Syndrome: A Study of North American Trauma Centers. Neurosurgery. 2024;94(4):700-710.
28.Sattari SA, Antar A, Theodore JN, Hersh AM, Al-Mistarehi AH, Davidar AD. Early versus late surgical decompression for patients with acute traumatic central cord syndrome: a systematic review and meta-analysis. Spine J. 2024;24(3):435-445.
29.Aarabi B, Akhtar-Danesh N, Simard JM, Chryssikos T, Shanmuganathan K, Olexa J. Efficacy of Early (≤ 24 Hours), Late (25-72 Hours), and Delayed (>72 Hours) Surgery with Magnetic Resonance Imaging-Confirmed Decompression in American Spinal Injury Association Impairment Scale Grades C and D Acute Traumatic Central Cord Syndrome Caused by Spinal Stenosis. J Neurotrauma. 2021;38(15):2073-2083.
30.Stanley AL, Jones TJ, Dasic D, Kakarla S, Kolli S, Shanbhag S. Five-year mortality after traumatic central cord syndrome in Wales. Bone Joint J. 2023;105-B(8):920-927.
Full reference list with DOI and PubMed links is available in the online references view.
Slides, notes and references
Scan for the full reference list with PubMed links, the speaker notes handout, and this deck.